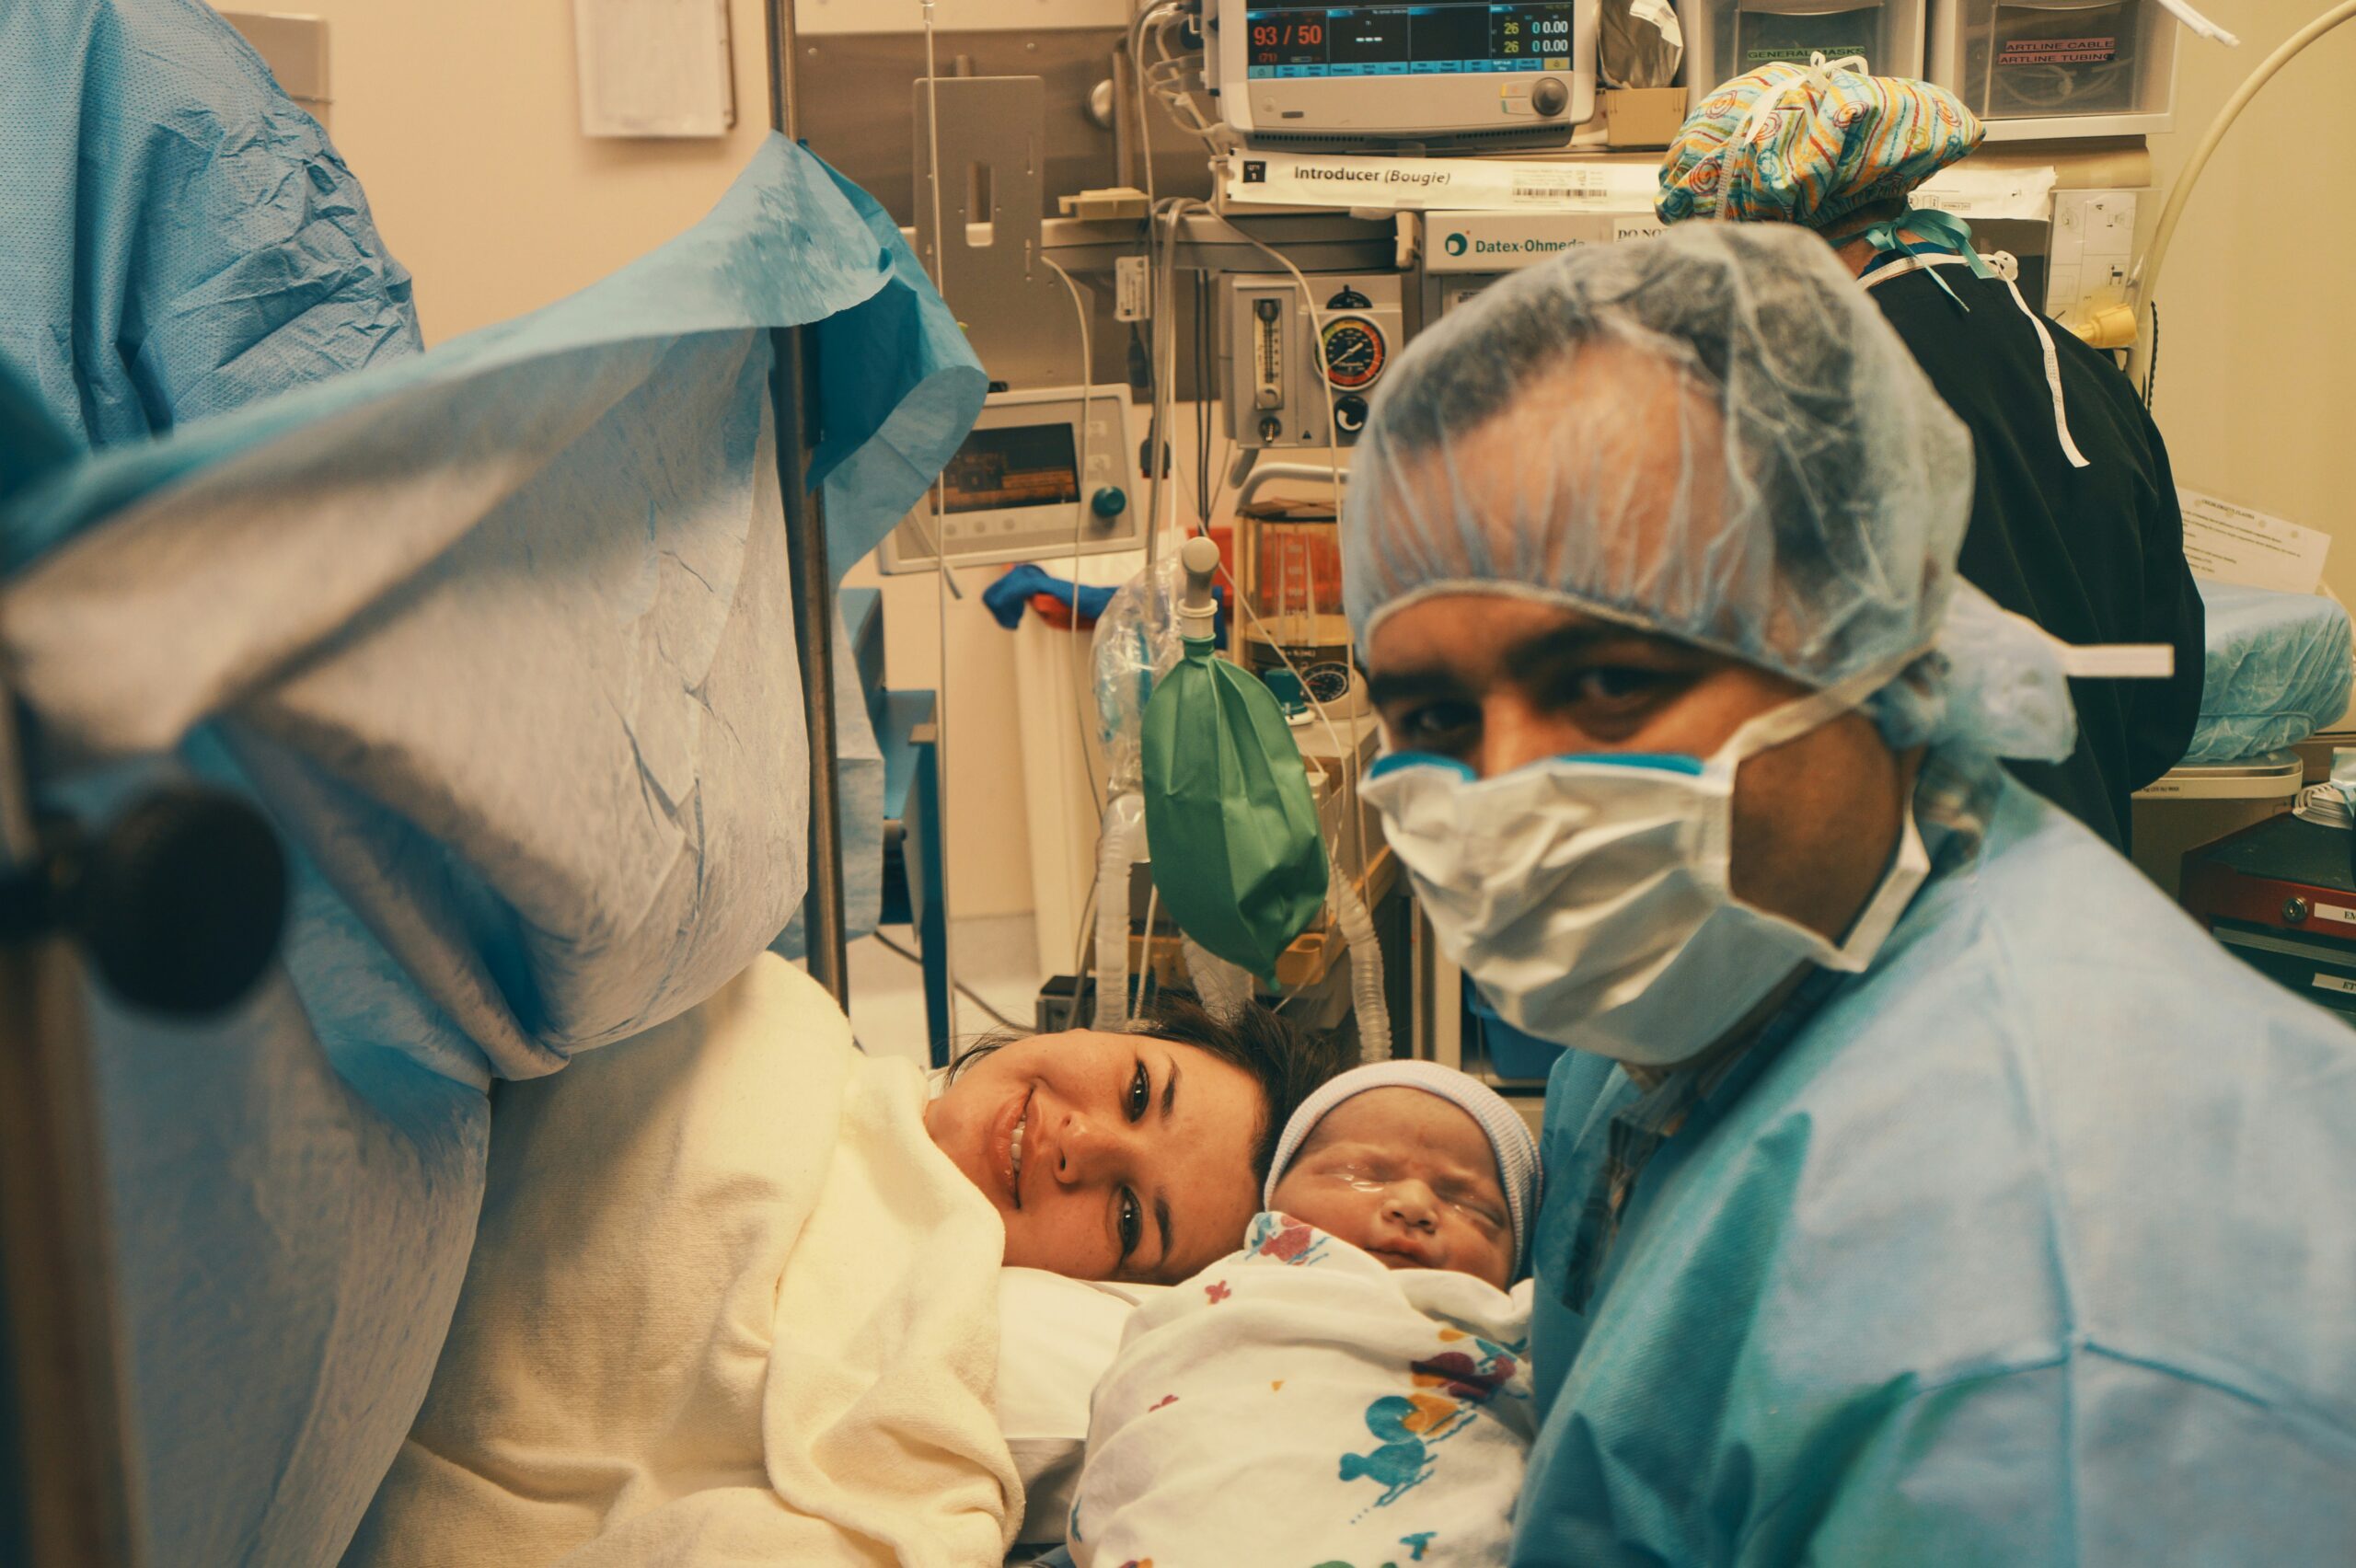
“Do I Have Trauma From My C-Section?” Caesarean Birth Trauma: What Happened, Why It Stays, and What You Can Do
After a traumatic caesarean · Part 1 (series guide) · 18 min read · Published 30 October 2026 · Reviewed 30 October 2026 · Next review April 2027
By Dr Rosemary Listing, PhD (Law) · Medical negligence lawyer since 2013 · Of Counsel, Peter Evans & Associates
In this guide
If your caesarean (c-section) left you shaking, replaying it at night, or feeling you can't tell anyone because “at least the baby's fine”, this guide is for you. It explains what usually happens in theatre and what should happen when it doesn't go to plan, why caesarean birth trauma is common and real, how to find out what happened from your records, and when a hard birth may also have been substandard care.
Quick answer · updated October 2026
Yes, a caesarean can be traumatic, planned or emergency, and you don't need anyone's permission to call it that. Feeling pain during the operation, being put to sleep, or being separated from your baby are common triggers. Trauma alone isn't negligence, but your records can show whether your care fell short. Start with your records.
Your caesarean, step by step
- 1On the tableNumbness, pain, urgency and who decides
- 2The first daysRecovery, separation and a debrief before you go home
- 3Six weeks onWhen the shock doesn't settle
- 4Finding outRecords, questions and an independent review
- 5What nextComplaint, claim, or the next pregnancy
At any stage: if you are not coping, call PANDA on 1300 726 306. If you are in crisis, call Lifeline on 13 11 14 or 000.
The drape was so close to my face I could see the weave in it. I'd been in labour for thirty-one hours. I'd stalled at six centimetres, the baby's heart rate kept dipping, and suddenly there were eight people in the room and someone was topping up my epidural.
When they started, I felt a line of fire low across my belly. I said I could feel it. The anaesthetist leaned over and said, “That's just pressure, love. You're doing great.” It wasn't pressure. I know what pressure is. I'd just had a day and a half of it.
I started shaking so hard my teeth knocked together. I remember my husband's hand going white around mine, and then a mask, and then nothing.
I woke in recovery, alone, with a nurse writing on a chart. My son was in the special care nursery. The first time I saw his face was on my husband's phone, a video of a tiny fist with a cannula taped to it. Everyone kept telling me how lucky we were. I kept saying yes.
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
This guide is for you if your caesarean has stayed with you: the planned one where the spinal wore off, the emergency one where you woke up “not pregnant”, or the one you felt pushed into after days of induction. It is also for partners who stood beside the bed, and for nurses and midwives who were the patient this time.
It covers what should happen in theatre, why trauma after a caesarean is so common, how to get answers, and how the law tells a frightening birth apart from care that fell short.
Why I can write this
I have been a medical negligence lawyer since 2013 and have worked on many hundreds of claims, a large share of them involving birth. My doctorate looked at patterns of failure in medical negligence. I'm not medically qualified. The clinical facts here are checked against named Australian sources, including RANZCOG's statements and guidelines, the federal Pregnancy, Birth and Baby service and the Centre of Perinatal Excellence (COPE), and each source is listed at the end. I'm writing for readers anywhere in Australia; where the law differs between states, I say so.
Start with your question
- “I felt my c-section. Is that normal?” → On the table and the full article on pain during a caesarean
- “They put me to sleep and I missed the birth.” → The first days
- “It's been months and I still can't stop replaying it.” → Six weeks on and PTSD after an emergency caesarean
- “I felt pushed into the induction and the caesarean.” → Induction, consent and an unplanned caesarean
- “Was something actually done wrong?” → Finding out what happened and getting an independent review
- “My partner watched it all and isn't okay.” → When your partner's caesarean traumatised you
- “Is it too late to ask?” → Time limits across Australia
- “I'm scared to have another baby.” → Pregnancy after a traumatic caesarean
On the table: what should happen, and what can go wrong
Around 4 in every 10 babies in Australia are now born by caesarean, according to national data from the Australian Institute of Health and Welfare. Routine for the hospital is not routine for you. It is major surgery, often done while you are awake, frightened and exhausted.
Most caesareans in Australia are done with a spinal or an epidural, so you are awake. Pregnancy, Birth and Baby explains that you can expect tugging and pulling, but should not feel pain, and that a general anaesthetic is used when the spinal or epidural isn't working, there isn't time, it isn't safe, or you ask for one.
Definition
Neuraxial anaesthesia is the umbrella term for a spinal, an epidural, or a combination of the two. Medicine is placed near the nerves in your lower back so the lower half of your body goes numb while you stay awake. An epidural used in labour can be “topped up” with stronger medicine for a caesarean.
In plain terms: it's the injection in your back that numbs you from the chest down. It should be checked and working before the first cut.
“It's just pressure”: when you can feel the operation
The most common thing women tell me is: I could feel it, and no one believed me. You are not imagining that this happens. A 2025 review of 34 studies, published in Anesthesiology, found that around 17% of women reported pain during a caesarean under spinal or epidural, with the highest rate (about one in three) when a labour epidural was topped up for surgery.
Pain during a caesarean is not, by itself, proof of negligence. Blocks sometimes fail even when everything is done well. The questions are what the team did before starting, and what they did when you told them. That is covered in depth in “I Felt My C-Section”.
How urgent was it? The four categories
Definition
Category of urgency is the label the team gives your caesarean when they decide to do it. RANZCOG's Categorisation of Urgency for Caesarean Section (C-Obs 14) uses four categories, from category 1 (an urgent threat to your life or your baby's) to category 4 (a planned time that suits you and the team).
In plain terms: the category tells you how much of an emergency the team believed it was, and it should be written in your notes.
Pregnancy, Birth and Baby says a category 1 caesarean usually happens within 30 minutes of the decision, and category 2 within 60. A RANZCOG O&G Magazine article on “crash” caesareans notes that RANZCOG prefers individual assessment to fixed time limits. It also notes that the urgency itself can be traumatic for the woman and her family.
Questions to ask about what happened in theatre
- What category was my caesarean, and why?
- How was my numbness checked before the operation started, and what was written down?
- When I said I could feel pain, what was done, and at what time?
- Was a general anaesthetic offered or considered, and if not, why not?
- Why was my baby taken out of the room, and was anyone told to update me?
The first days: put to sleep, separated, alone in recovery
Many women describe the same sequence: the decision, the rush, the cold theatre, then a gap. Some woke from a general anaesthetic not knowing whether their baby was alive. Others were awake but shaking, and saw their baby for a second over the drape.
If you were asleep for the birth, there may be gaps you can't fill on your own. That's covered in I Don't Remember My Baby's Birth. If your baby went to special care, you may have missed the first feed, the first cuddle, the first everything, and felt guilty for grieving that when they survived.
RANZCOG's 2025 guideline on birth after caesarean (C-Obs 38) suggests that women who have an unplanned caesarean are offered a debrief before they leave hospital. It suggests the debrief be both spoken and written, explaining why the caesarean happened and what your options are next time. It also suggests offering a referral if there are concerns about your psychological wellbeing. Many women tell me no one offered one. If that happened to you, you can still ask for one now: see How to Ask for a Birth Debrief.
Six weeks on: when the shock doesn't settle
Feeling shaken in the first days is common. What matters is what happens after that. Pregnancy, Birth and Baby describes postpartum PTSD as distress that continues for more than four weeks after a traumatic birth. It names emergency caesarean as one possible cause, and extreme pain, loss of control and fear of death as risk factors.
Definition
Post-traumatic stress disorder (PTSD) is a mental health condition that can follow an experience where you, or someone you love, faced serious harm. Common signs include reliving the event through flashbacks or nightmares, avoiding reminders, feeling constantly on edge, and feeling numb or cut off. A doctor or psychologist diagnoses it.
In plain terms: your body is still treating the operating theatre as if it's happening now.
Women describe it in very ordinary moments: the squeeze of a blood pressure cuff at the GP, the smell of hand sanitiser, a hospital car park, the baby's first birthday. A 2022 review across 154 studies found that about 4.7% of mothers meet the criteria for PTSD after birth, and about 12.3% have significant post-traumatic stress symptoms. Partners are affected too.
The good news is that there is effective treatment. COPE lists trauma-focused cognitive behaviour therapy (CBT), eye movement desensitisation and reprocessing (EMDR) and, where needed, medication. Your GP can refer you to a perinatal psychologist, and the free and low-cost support guide lists services that don't need a referral. If people keep saying “at least the baby's healthy”, read this article on the things people say.
The full guide to this stage is “I Can't Get Over My Emergency C-Section”.
If you felt pushed into it
A second, quieter kind of trauma comes from feeling that decisions were made to you rather than with you: the induction you didn't want, the “big baby” warning that turned out not to be true, the consent form signed between contractions. RANZCOG's 2026 statement on consent says you are entitled to information about the benefits, risks and alternatives of a treatment, and that you may refuse it or withdraw your consent at any time, including during the procedure. In a true emergency, consent may be verbal. Pregnancy, Birth and Baby's guide to your rights explains this in plain language, and “I Felt Pushed Into It” goes further.
If you were the partner, or you work in health
Partners often carry the picture no one else saw: the blood, the silence before the cry. Gidget Foundation notes that people who witness a traumatic birth can be traumatised too. That's covered in “I Thought I Was Watching Her Die”. If you are a nurse, midwife or doctor, knowing exactly what was going wrong can make it worse, not better. Your article is “I'm a Nurse and They Still Didn't Listen”.
Finding out what happened
For most people, the turning point is finally understanding the timeline. You are entitled to your records, and don't need a reason to ask. My guide to getting and reading your birth records explains how, and a debrief with someone who can walk you through them can help a great deal. If you went through instruments before the caesarean, this article on failed instrumental births explains that part of the record. If your baby was affected, see “Why Didn't They Do a Caesarean Sooner?”.
Some women then want an independent person to read the file and tell them, honestly, whether the care was reasonable. That is what “Was Something Done Wrong?” is about. Sometimes the answer is that everyone did their best, and many women find that healing too.
Trauma, or negligence? They are different questions
Your trauma is real whether or not anyone was at fault. A claim, though, needs three things together.
The care fell short
What was done, or not done, was below what was widely accepted as competent practice at the time, or you weren't told about a material risk.
In plain terms: a reasonable team would have acted differently.
It made a difference
The shortfall caused or contributed to your injury, judged on the balance of probabilities.
In plain terms: with proper care, this harm probably wouldn't have happened.
You were harmed
A physical injury, a psychiatric injury such as PTSD, or both, with effects on your life, work or family.
In plain terms: it left a mark that can be measured.
If you aren't sure which of these applies to you, that's normal. It's exactly what a free case review is for.
What next: complaint, claim, or the next pregnancy
A complaint asks the hospital to explain and to change things. You can complain to the hospital first, then to the health complaints body in your state or territory. Ahpra keeps a list of every state's body, from the Health Care Complaints Commission in NSW to the Office of the Health Ombudsman in Queensland. See whether to complain, with a free template. A claim asks for compensation for what the harm has cost you. They can run side by side, and a complaint doesn't stop you making a claim later.
The next pregnancy is its own decision. Some women want a planned repeat caesarean with a very different plan; others want to try for a vaginal birth after caesarean (VBAC). RANZCOG's 2025 guideline says clinicians should give non-directive information about the risks and benefits of each option, and respect your preferences. “I'm Scared to Have Another Baby” covers this stage.
Eight months later, I was at the GP for my son's vaccinations when the nurse wrapped a blood pressure cuff around my arm for a quick check. When it squeezed, I was back on the table. I couldn't breathe. My son was screaming on my lap and I couldn't move.
The GP sat with me afterwards. She didn't say “at least he's healthy”. She said, “That sounds like it was very frightening. Have you ever been told what happened?” I hadn't.
I asked for my records. The anaesthetic chart had a line that read “pt anxious, reassured”, timed nine minutes before the general anaesthetic. Nothing about pain. Reading that was awful, and strangely steadying. It was on paper.
A midwife from another hospital went through the timeline with me, minute by minute. I'm seeing a perinatal psychologist now. Some days I can drive past the hospital without my hands shaking.
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
What to look for in the records
Ask for the complete file, not a summary. These are the parts that usually matter most after a traumatic caesarean.
| Record | Why it matters |
|---|---|
| Operation note | The category of urgency, the reason for the caesarean, the type of cut, any complications, and the surgeon's account of what happened. |
| Anaesthetic record | Whether a spinal, epidural top-up or general anaesthetic was used; how and when numbness was checked; extra doses; and any note of you reporting pain, with times. |
| Theatre and birth times | The time the decision was made, the time of the first cut, and the time of birth. Gaps here can matter. |
| CTG (fetal heart tracing) and partogram | What led to the decision, and whether warning signs were acted on promptly. |
| Consent form and notes of discussions | What risks and alternatives were recorded, when, and whether consent was written or verbal. |
| Intraoperative nursing record | Who was present, the swab and instrument count, and events in theatre. |
| Recovery and postnatal notes | Pain scores, how long you were alone, when you met your baby, and whether a debrief was offered. |
| Baby's special care or NICU records | Why your baby was taken away and their condition at birth. These are your baby's records, and may need a separate request. |
If something seems to be missing, write down what you remember now, with dates. Your memory is evidence too.
How the law looks at it
The principles below apply across Australia, though each state and territory has its own legislation, and the details can matter.
Standard of care. A health professional isn't negligent just because something went wrong. In NSW, section 5O of the Civil Liability Act 2002 (NSW) says a professional isn't liable if they acted in a way that was widely accepted in Australia by peer professional opinion as competent practice, unless the court finds that opinion irrational. Most other states have a similar rule; the ACT and the Northern Territory rely on the common law. Guidelines like RANZCOG's are evidence of what competent practice looks like. They are not the law itself, and departing from one isn't automatically negligent.
Causation. You also need to show, on the balance of probabilities, that the shortfall caused your harm. In Tabet v Gett [2010] HCA 12, the High Court held that losing a chance of a better outcome is not enough on its own. In plain terms: it has to be more likely than not that proper care would have made a difference.
Consent. In Rogers v Whitaker [1992] HCA 58, the High Court held that doctors must warn patients of material risks: risks a reasonable person would think significant, or that this patient would. In NSW, the peer-opinion defence in section 5O does not apply to the duty to warn.
Who can claim. A mother can claim for physical injury and for psychiatric injury such as PTSD. A partner who witnessed the birth may, in some circumstances, have their own claim for a recognised psychiatric illness, but the rules on this differ markedly between states. A baby injured at birth has their own separate claim.
Time limits. Time limits apply, and they differ by state. For children, they don't always wait until the child turns 18. The safest course is to ask early. See time limits across Australia and, if your care was in NSW, the NSW time limits guide. What a claim can cover is explained in the compensation guide.
In my practice
When I read the file in a traumatic caesarean, I rarely find one dramatic mistake. I find a chain of small failures that line up. The category is escalated, so the numbness is checked in a hurry, or not recorded. A woman says she can feel it, and the chart says “anxious, reassured”. The baby goes to special care and no one is tasked with telling the mother. She leaves without a debrief, and first learns why it happened from her own records, months later, at the kitchen table. Each link might be defended on its own. Together they explain why a “successful” operation can leave a woman feeling something was done to her. My work is to separate the links that were unavoidable from the ones that weren't.
Both things can be true
You can be deeply grateful that your baby is alive, and still be harmed by how you were treated. The team may have saved your child's life, and still not listened when you said you could feel the knife. Holding both isn't ingratitude or blame. It's the starting point for healing and, sometimes, for asking that it be done differently.
The bigger picture
The NSW Parliament's Select Committee inquiry into birth trauma heard from thousands of women and reported in 2024 with 43 recommendations, including on informed consent and trauma-informed care. RANZCOG now suggests a debrief after every unplanned caesarean, and research shows pain during caesarean is more common than many women are told. A legal claim is only one of the ways things change.
Support
- PANDA National Perinatal Mental Health Helpline: 1300 726 306, for mothers and partners, seven days a week.
- Gidget Foundation Australia: 1300 851 758, free psychological support for expectant and new parents, including after birth trauma.
- Birth Trauma Australia: peer support and information, including on recovery after a caesarean.
- Miracle Babies Foundation NurtureLine: 1300 622 243, 24 hours, for families whose baby was in special care or NICU.
- Pregnancy, Birth and Baby: 1800 882 436, to speak with a maternal child health nurse.
- Lifeline: 13 11 14, 24 hours, if you are in crisis. In an emergency, call 000.
The woman in the stories still doesn't love hospitals. But she knows now what happened in that room, and that what she felt was real. She has started to plan how the next birth, if there is one, will be different.
With care,
Rosemary
Frequently asked questions
Is it normal to feel pain during a c-section?
You should feel tugging, pulling and pressure, but not pain. Pain under a spinal or epidural happens more often than many people realise, and when you report it, the team should take it seriously and act.
Can you get PTSD from a c-section?
Yes. Emergency caesarean, extreme pain, loss of control and fear for your baby's life are all recognised risk factors. If distress continues beyond about four weeks, talk to your GP.
Can I sue if I felt my c-section?
Possibly. Feeling pain isn't automatically negligence. The question is whether the anaesthetic was properly checked and whether the team responded reasonably when you told them. Your anaesthetic record is the key document.
Is an emergency c-section the same as an unplanned one?
Not always. Hospitals classify urgency in four categories. Your category, and the reason for it, should be written in your notes.
How long do I have to make a claim after a caesarean?
It depends on your state and your circumstances. Time limits can be shorter than people expect, so ask early.
Can my partner claim for trauma from watching my c-section?
Sometimes. A partner who develops a recognised psychiatric illness after witnessing the birth may have a claim, but the rules vary by state and are strict.
Questions about your caesarean?
When you're ready, and not before, you can ask me to look at what happened. There's no cost and no obligation to go further.
After a traumatic caesarean: the series
- “Do I Have Trauma From My C-Section?” Caesarean birth trauma (you are here)
- “Is It Too Late?” C-section negligence: time limits across Australia and what a claim can cover
- “I Felt My C-Section”: pain during a caesarean
- “I Can't Get Over My Emergency C-Section”: PTSD, flashbacks and getting help
- “I Felt Pushed Into It”: induction, consent and an unplanned caesarean
- “Was Something Done Wrong?” Getting an independent review of your c-section
- “I Thought I Was Watching Her Die”: when your partner's c-section traumatised you
- “I'm a Nurse and They Still Didn't Listen”: c-section trauma when you work in health
- “I'm Scared to Have Another Baby”: pregnancy after a traumatic c-section
Related: The Caesarean Injuries No One Warns You About · The birth injury map · Birth trauma and obstetric negligence
References
- Australian Institute of Health and Welfare. Australia's mothers and babies: Method of birth.
- Pregnancy, Birth and Baby (Healthdirect Australia). Caesarean birth (C-section). Last reviewed December 2025.
- Pregnancy, Birth and Baby. Emergency caesarean. Last reviewed December 2025.
- Pregnancy, Birth and Baby. Postpartum PTSD. Last reviewed May 2025.
- Pregnancy, Birth and Baby. Informed consent and your rights when having a baby.
- RANZCOG. Statements and Guidelines, including Categorisation of Urgency for Caesarean Section (C-Obs 14), 2019.
- RANZCOG. Birth After Caesarean (C-Obs 38), Clinical Guideline, version 4.1, August 2025.
- RANZCOG. Consent and provision of information to patients regarding proposed treatment (C-Gen 2), June 2026.
- Sleeman M. Crash caesarean. O&G Magazine 2017;19(2).
- Charles EA, Carter H, Stanford S, et al. Intraoperative pain during cesarean delivery under neuraxial anesthesia: a systematic review and meta-analysis. Anesthesiology 2025.
- Heyne CS, Kazmierczak M, Souday R, et al. Prevalence and risk factors of birth-related posttraumatic stress among parents: a comparative systematic review and meta-analysis. Clinical Psychology Review 2022;94:102157.
- Centre of Perinatal Excellence (COPE). Birth trauma: information for health professionals.
- Gidget Foundation Australia. Understanding birth trauma.
- Ahpra. Other health complaints organisations.
- Parliament of NSW, Legislative Council. Select Committee on Birth Trauma: inquiry details and report, 2024.
- Civil Liability Act 2002 (NSW), ss 5D, 5O, 5P.
- Tabet v Gett [2010] HCA 12; (2010) 240 CLR 537.
- Rogers v Whitaker [1992] HCA 58; (1992) 175 CLR 479.
- Birth Trauma Australia. Post-traumatic stress disorder (PTSD) and Caesarean section.
- PANDA. National Perinatal Mental Health Helpline.
- Miracle Babies Foundation. Birth trauma.
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
About the author
Dr Rosemary Listing, PhD (Law), has been a medical negligence lawyer since 2013 and is Of Counsel at Peter Evans & Associates. Her doctorate examined patterns of failure in medical negligence, and she teaches health law at the University of Newcastle. She is not medically qualified; clinical information in this article is checked against the Australian sources listed above.
Last updated: 30 October 2026 · First published: 30 October 2026 · Next review: April 2027
Cite this article: Listing, R. (2026). “Do I Have Trauma From My C-Section?” Caesarean Birth Trauma: What Happened, Why It Stays, and What You Can Do. Reframe Legal. https://reframelegal.com/c-section-trauma/
This article is general information, not legal or medical advice. Every situation is different, and time limits and laws vary between states and territories. If you are in immediate danger, call 000. If you need someone to talk to now, call Lifeline on 13 11 14.
Legal services are provided by Peter Evans & Associates.