HIE After Birth: A Guide for Parents, From the Cooling Cot to the Answers
Birth injury to babies · 18 min read · Published 28 October 2026 · Reviewed 28 October 2026 · Next review April 2027
By Dr Rosemary Listing, PhD (Law) · Medical negligence lawyer since 2013 · Of Counsel, Peter Evans & Associates
Your baby's journey after HIE
Where are you right now? Tap a point on the timeline.
The first hour
Your baby is resuscitated and stabilised first: breathing, circulation and blood sugar. If the birth was difficult, the team should take blood from the cord to measure how much oxygen your baby was short of, and check your baby's tone, breathing and alertness.
"Everyone went quiet, then the room filled with people."
Questions to ask
- Were cord gases taken? What were the results?
- What were my baby's Apgar scores at 1, 5 and 10 minutes?
- How long did resuscitation take?
The six-hour window
Babies at risk of HIE should be examined every hour for signs of encephalopathy. If your baby is 35 weeks or more and meets the criteria, the team calls the newborn retrieval service (NETS in NSW, PIPER in Victoria) to arrange cooling, and may start careful passive cooling while they wait.
"They kept saying 'just to be safe'. Nobody said the word cooling."
Questions to ask
- Is my baby being checked for encephalopathy? How often?
- Does my baby meet the criteria for cooling?
- Has the retrieval team been called? What time?
Cooling
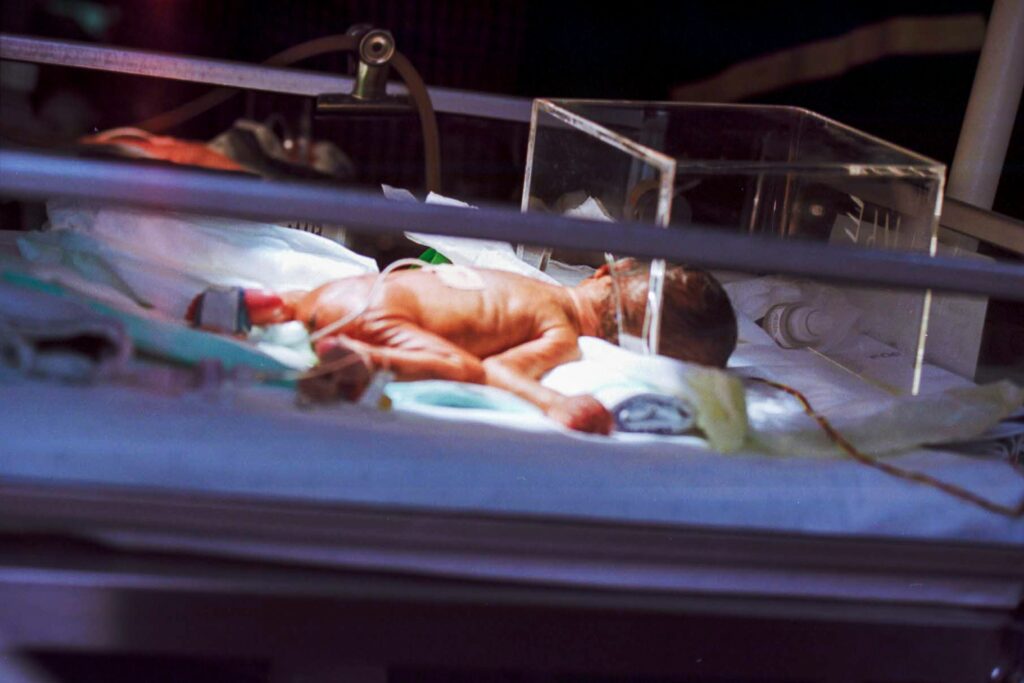
Your baby lies on a cooling mat or wrap that holds their core temperature steady, usually with a brain-wave monitor (EEG) and often a breathing machine. Seizures are common and are treated with medicine. Many parents can't hold their baby yet, but you can still touch, talk, help with care and express milk.
"I zoomed in on 33.5°C on the photo, trying to work out if it was good or bad."
Questions to ask
- What time did cooling start, and when did it reach target?
- Has my baby had seizures? Seen, or only on the monitor?
- Can I touch my baby, change nappies, or hold my baby?
Rewarming and the MRI
Your baby is warmed slowly over several hours and watched closely. For many families this is the first cuddle. An MRI is usually done in the first week or two, and the grade (mild, moderate or severe) may be revised as your baby is examined again.
"Moderate at birth, then mild after the MRI. I didn't know which one to believe."
Questions to ask
- When is the MRI, and who will explain the result to us?
- Which parts of the brain does the report mention, and what do they do?
- Can we have a copy of the MRI and EEG reports?
Coming home
Feeding is often what keeps families in hospital. Some babies go home with a nasogastric (NG) tube. Before discharge you should be booked into follow-up, usually a high-risk infant clinic, and told how to get therapy started.
"Feeding was the last thing standing between us and the front door."
Questions to ask
- Who follows my baby up after discharge, and when is the first appointment?
- Can you refer us to physio, OT and speech now?
- Who do we call if we're worried at home?
The long wait
Many effects of HIE only show as a baby grows, so you will hear "wait and see". But waiting doesn't have to mean waiting until two: cerebral palsy, or a high risk of it, can often be predicted before six months, so therapy can start early.
"I spent the first six months watching him instead of enjoying him."
Questions to ask
- Has my baby had a General Movements Assessment or HINE?
- What signs should we watch for, and what is normal variation?
- Can we be referred for an early diagnosis assessment?
The answers
Some parents want to know what happened straight away; others wait years. The records hold the timeline: the heart rate trace, the cord gases, the hourly checks and the time of every call. In NSW, cooled babies should be reported through the hospital's incident system, and you can ask to hear the review's findings.
"For months I thought I should have pushed. None of those decisions were mine to make."
Questions to ask
- Has my baby's birth been reported and reviewed?
- Can we have a copy of the full maternity and NICU records, including the CTG?
- Can we meet to go through what happened?
General information from the NSW, Victorian and Queensland newborn guidelines. Times are typical and vary for every baby. Your baby's team is the right source for anything about your baby.
Hypoxic-ischaemic encephalopathy (HIE) is a brain injury in a newborn caused by a lack of oxygen or blood flow around the time of birth. In Australia, babies born at 35 weeks or later with moderate or severe HIE are usually offered cooling, ideally started within six hours. What happens next ranges from no lasting effects to serious disability, and many answers take months. This guide walks through the five stages parents tell me they go through, from the first week to finding out what happened, and links to a detailed article for each question.
HIE is a brain injury caused by a lack of oxygen or blood flow around birth. Babies of 35 weeks or more with moderate or severe HIE are usually cooled to 33 to 34°C for about 72 hours, starting within six hours of birth. Outcomes range widely, from no lasting effects to serious disability, and many questions can't be answered for months. HIE can follow excellent care, and some HIE is preventable.
"Downstairs, my mum was still texting everyone. She's here! 3.4 kilos! People were sending flowers. Upstairs, at two in the morning, a doctor I'd never met pulled the curtain around my bed and said three letters I'd never heard: H, I, E.
I nodded the whole time. I said 'okay' about twenty times. When she left, I couldn't have told you a single thing she'd said, except that they were making my daughter cold on purpose and I wasn't allowed to pick her up.
I got out my phone and typed the letters into Google with my thumb. Every result was either a lawyer or a baby who had died. I put the phone face down on the blanket and just lay there, listening to the woman in the next bed feeding her baby."
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
If that is where you are now, in a ward bed or a NICU chair or awake at home at 3 a.m., I am so sorry. I wrote this guide for that moment, and for all the moments after it. It starts with what HIE is, then follows the order parents actually live it: the first week, the results, coming home, the long wait, and, for some families, the questions about what went wrong.
You don't need to read it all. Find your question below and go straight there.
I am a medical negligence lawyer, not a doctor. I have practised since 2013 and worked on many hundreds of claims, including for families after injuries at birth. My doctoral research looked at patterns of failure in medical negligence: how harm in health care usually comes from chains of small things. Everything clinical here is drawn from, and checked against, the Australian neonatal guidelines listed at the end. It is general information. Your baby's own team is the right source for anything about your baby.
- "Why is my baby being cooled, and when can I hold her?" · The first week in NICU
- "They said moderate, now they're saying mild. Which is it?" · What your baby's HIE grade means
- "Why wasn't my baby cooled?" · When cooling was late, missed or not offered
- "What does 'basal ganglia' mean on the MRI?" · Reading your baby's MRI and EEG
- "Will my baby be okay?" · Living with "wait and see"
- "Could this have been prevented?" · Could my baby's HIE have been prevented?
- "How long do we have to do anything about it?" · Time limits and compensation
What HIE is
Hypoxic-ischaemic encephalopathy (HIE) · Brain dysfunction in a newborn caused by a lack of oxygen in the blood (hypoxia) and/or reduced blood flow to the brain (ischaemia) from an event around the time of birth. Doctors grade it as mild, moderate or severe.
In plain terms: for a period of time, during labour, at birth or just after, your baby's brain didn't get enough oxygen. "Encephalopathy" just means the brain isn't working as it normally would, which doctors can see in how alert your baby is, how they move and feed, and whether they have seizures.
Sometimes HIE follows a sudden emergency: the uterus tearing (uterine rupture), the placenta coming away early (placental abruption), the cord slipping down ahead of the baby (cord prolapse), or a baby's shoulders getting stuck at birth (shoulder dystocia). Sometimes it builds more slowly, over hours of labour in which the baby's oxygen reserves run down. Sometimes no clear cause is ever found. And in a small number of babies who are first thought to have HIE, a different cause turns up later: a 2026 study from one tertiary NICU found about 1 in 10 cooled babies had another explanation, such as a metabolic or genetic condition.
HIE is not rare, and you are not the only family going through this. The NSW Agency for Clinical Innovation guide reports that 358 babies born after 34 weeks in the Australian and New Zealand neonatal network were cooled in 2020.
Mild, moderate and severe · The grade is based on a structured examination of your baby's level of alertness, muscle tone, reflexes, breathing and any seizures in the first hours. Many units use a version of the Sarnat score.
In plain terms: the grade is a snapshot of how your baby's brain was working in those first hours. It guides whether cooling is offered. It can change as your baby is examined again, and on its own it does not tell you how your baby will grow up.
Stage 1 · The first week
If your baby is 35 weeks or more and has moderate or severe encephalopathy in the first six hours, the team will usually offer cooling, also called therapeutic hypothermia. Your baby's core temperature is lowered to 33 to 34°C and held there for about 72 hours, then brought back up slowly. The NSW guide expects at-risk babies to be checked every hour for those first six hours, and the newborn retrieval service (NETS in NSW, PIPER in Victoria) to be called early, because cooling works best when it starts early.
The evidence for cooling is strong. A Cochrane review led by Melbourne neonatologist Susan Jacobs pooled the major trials and found that cooling reduces death and major disability in babies with moderate or severe HIE. Queensland's HIE guideline, reissued in July 2026, sets out the same core approach as NSW and Victoria.
The first week is often the hardest. Babies may be on a breathing machine, have seizures that need medicine, and be covered in wires for brain monitoring. Mothers are often recovering in a different hospital. Many parents can't hold their baby until after rewarming. My guide to cooling, rewarming and the first week in NICU goes through it hour by hour, with the questions to ask and the things you can still do for your baby. If your baby wasn't cooled, or cooling started late, my guide to babies who weren't cooled explains how the criteria work and when that deserves a closer look.
Stage 2 · The results
Most cooled babies have an MRI in the first week or two, after rewarming, and an EEG (a recording of brain activity) during and after cooling. The MRI report is the moment many parents dread. It may describe injury to particular parts of the brain, such as the basal ganglia and thalamus (deep structures involved in movement) or the watershed areas (the outer zones between the brain's main blood supplies). The pattern can say something about how and when the injury happened, which matters later if you want to know what went wrong.
It is common for the grade to change, and for the MRI not to match how your baby seems. Parents tell me, again and again, that two babies with similar scans went on to do very differently. My guides to what your baby's HIE grade means and reading the MRI and EEG reports explain the words in plain language, and the questions to ask the neonatologist or neurologist when they go through the results with you.
Stage 3 · Coming home
For many families, feeding is what keeps them in hospital. Babies after HIE may struggle to suck and swallow safely, and some go home with a nasogastric (NG) tube, or later a gastrostomy (G-tube). My guide to feeding after HIE covers what parents in this stage ask most.
Before you leave, you should be told about follow-up: usually a high-risk infant follow-up clinic, with regular developmental checks for at least the first two years. If your baby has, or may have, developmental delay, the NDIS early childhood approach supports children younger than 9 and their families. My guide to early intervention after HIE explains how to get physio, occupational therapy and speech therapy started, and who pays.
Stage 4 · The long wait
"Wait and see" is the phrase parents hate most, and the one they hear most. It is honest, because many effects of HIE only show as a baby grows. But it can make it very hard to simply be with your baby.
"I found this site three months in, at about 4 a.m. I'd been up with a bottle and I was doing what I did every night, which was watching his hands. Is he keeping his thumbs tucked in? Is he looking at me, or past me? Is that a normal kick or a stiff one?
Everyone told us he was doing well. The physio said he was doing well. My partner said he was doing well. And he was. But the neonatologist had said 'we won't really know until he's two', and that was the only sentence my brain kept.
What helped, in the end, was writing down what I was worried about and taking the list to the follow-up clinic, instead of checking him all night. Some things they ticked off. One thing they referred on. It was the first time in three months I felt like I was doing something, rather than just watching."
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
Here is something Sam didn't know, and many parents don't. Waiting no longer has to mean waiting until two. Research led by Australian cerebral palsy researcher Iona Novak, published in JAMA Pediatrics in 2017, found that cerebral palsy, or a high risk of it, can be accurately predicted before six months' corrected age using an MRI, a video assessment of a baby's movements (the General Movements Assessment) and a structured neurological examination (the HINE). An early diagnosis means earlier therapy. Cerebral Palsy Alliance runs a free early diagnosis clinic for babies up to 12 months' corrected age.
My guides to living with "wait and see" and early signs, milestones and a cerebral palsy diagnosis cover what to watch for, what is normal variation, and how to ask for an assessment rather than wait.
And because so many of you are searching for this: many babies who are cooled for HIE grow up with no lasting effects, or with effects that are mild. Some have serious, lifelong disability. Both are true, and nobody can honestly tell you in the first weeks which your baby will be.
Stage 5 · The answers
For some families, the questions about what happened start in the NICU. For others they come months or years later, often at 3 a.m., often as guilt. Should I have gone in earlier? Should I have said something when the heart rate dropped? My guide for parents who keep replaying the birth is about that, for mothers and for partners.
The decisions in labour and in those first hours were not yours to make. They belonged to the clinicians caring for you, measured against standards like these:
- RANZCOG, the college that trains and sets standards for Australian obstetricians, sets out how a baby's heart rate should be monitored, interpreted and acted on in its Intrapartum Fetal Surveillance guideline (5th edition, 2025).
- The NSW ACI guide sets out how at-risk babies should be recognised, checked hourly and referred for cooling.
- The NSW Incident Management policy requires serious incidents to be reported and reviewed, and the family to be offered the findings.
If you want to understand whether something went wrong, the first step is nearly always the records: the CTG (heart rate trace), the cord blood gases, the observation charts and the timing of each call. My guides to getting the records and finding out what happened and whether your baby's HIE could have been prevented explain what to ask for and what an independent expert would look at. You can also ask the hospital for a birth debrief, and under the Australian Open Disclosure Framework the hospital should talk to you honestly when a patient has been harmed. If you want an independent body to look at the care, the NSW Health Care Complaints Commission handles complaints about health services, and our guide to making a complaint after a traumatic birth includes a free template.
"For a long time I didn't want to know. She was doing physio twice a week, she'd just started rolling, and I thought, why would I go back there?
What changed my mind was a letter from the hospital about a review. It said the review had found 'opportunities for improvement'. That was all. I read it standing at the letterbox and I thought, improvement on what?
When I finally sat down with the records, it wasn't one big thing. It was a lot of small things in a row, at times I'd never been told. I'm still not sure what I want to do about it. But I'm not lying awake guessing any more."
A composite story, drawn from the experiences of many families I have worked with, combined and changed so that no one can be identified. It does not describe any individual client.
How the law looks at HIE
A medical negligence claim for HIE is usually brought on behalf of the child, and sometimes also by a parent for their own injury, such as psychological harm. In broad terms, it has to show two things.
That the care fell below the accepted standard. In NSW, section 5O of the Civil Liability Act 2002 says a professional is not negligent if they acted in a way widely accepted by peer professional opinion as competent practice, unless that opinion is irrational. In HIE cases, independent obstetric and midwifery experts usually comment on the labour, and a neonatologist on the care after birth.
That this caused, or made worse, the injury. This is often the hardest part. A paediatric neurologist or neuroradiologist usually looks at the MRI pattern, the cord gases and the timeline to say when the injury most likely happened, and whether earlier action would have made a difference.
Information is part of care too. In Rogers v Whitaker, the High Court made clear that patients are entitled to the information a reasonable person would want about material risks, and that includes decisions in labour.
A good outcome doesn't always mean there's nothing to look at. Some families are told there is "no case because he's fine", and later find that problems with speech, learning or attention appear at school age. My guide to claims when your baby is doing well explains why the answer depends on the injury and how it affects your child as they grow.
Time limits for children work differently from those for adults, and differ between states. They are generally more generous for a child's own claim, but evidence fades: CTG traces, staff memories and equipment logs don't keep forever. Our guide to NSW time limits sets out the general rules, and my guide to time limits and compensation for a baby's HIE claim explains how they apply to children and what compensation is meant to cover. It is always better to ask early than to wait.
In my practice
The parents I speak with after HIE almost never start by asking about a claim. They start with "nobody told us anything", or "I just want to know if it was my fault". Usually, by the time they call me, they have read every forum post there is, and they have been told by well-meaning people that it was "just one of those things".
Sometimes it was. HIE does happen after excellent care, and when that is what the records show, I tell families so plainly, because that answer matters too. But my doctoral research, and many years of reading birth records, have shown me how often serious harm in health care comes from a chain of small things rather than one dramatic mistake: a trace noted as "suspicious" and not escalated, a registrar caught in theatre, a cord gas not taken, a call to the retrieval team made at hour five instead of hour two. Each link can look small on its own. Together, they can change a child's life. That is why the records from the first hours matter so much, and why it is worth getting them while everything is still fresh. Our guide to getting and reading your birth records explains how.
Both/and: HIE can follow excellent care, and some HIE is preventable
Both things are true. Some babies are injured by events nobody could have predicted or stopped in time, and the teams who resuscitate and cool them do extraordinary work. And some HIE follows warning signs that were missed, delays in getting a baby born, or delays in starting cooling. You can be deeply grateful to the people who saved your baby and still want to know whether it had to happen. Asking that question is not ingratitude. It is how the system learns.
The bigger picture
In 2024, the NSW Legislative Council's Birth Trauma inquiry found that much birth trauma stems from avoidable and preventable factors, and heard repeatedly from parents who felt shut out of information about their own births. NSW's HIE guidance itself grew out of a consensus statement by the Clinical Excellence Commission, written so that HIE would be recognised consistently in every hospital, not just the big ones. Our birth injury map shows how HIE connects to the injuries mothers suffer in the same births, such as haemorrhage, uterine rupture and complications of pre-eclampsia.
Support
- Miracle Babies Foundation: NurtureLine 1300 622 243, 24 hours, for families of sick and premature newborns, including in-hospital peer support.
- Life's Little Treasures Foundation: information, care packs and NICU Connections groups.
- Cerebral Palsy Alliance: the early diagnosis clinic and information for families, 1300 888 378.
- PANDA (Perinatal Anxiety & Depression Australia): 1300 726 306, or panda.org.au. For you and your partner.
- Birth Trauma Australia: birthtrauma.org.au.
- Our guide to finding support after birth trauma, much of it free.
Tess still has the screenshot of her mum's text: She's here! For months she couldn't look at it. Now it is her lock screen. "She was here," she told me. "She still is. Everything else, we're working out." Wherever you are in this, at the cooling cot or years down the track, you don't have to work it out on your own.
With care,
Rosemary
Frequently asked questions
What is HIE in a newborn?
Hypoxic-ischaemic encephalopathy is brain dysfunction in a newborn caused by a lack of oxygen or blood flow around the time of birth. It is graded as mild, moderate or severe based on how the baby is in the first hours.
Will my baby be okay?
Nobody can tell you for certain in the first weeks. Many babies cooled for HIE have no lasting effects or mild effects; some have serious disability. The MRI, follow-up checks and how your baby develops over months give a clearer picture, and cerebral palsy can now often be predicted before six months.
Is HIE always someone's fault?
No. HIE can follow sudden events nobody could have prevented, and a few cooled babies turn out to have a different cause. But some HIE follows missed warning signs or delays in birth or cooling. The records and an independent expert review are how you find out.
Can we make a claim for HIE?
A claim may be possible if the care fell below the accepted standard and that caused or worsened your baby's injury. It is usually brought on the child's behalf. It depends on the records, expert opinion and how your child is affected as they grow.
How long do we have to make a claim?
Time limits for children are generally more generous than for adults and vary between states, but evidence fades with time. It is best to get advice early, even if you are not sure you want to do anything yet.
Should the hospital be reviewing what happened?
In NSW, babies who are cooled or have moderate or severe HIE should be reported through the hospital incident system, and serious incidents reviewed. You can ask whether your baby's birth has been reported and ask to hear the findings.
Questions about your baby's care?
When you're ready, and not before, we can talk through what happened and look at the records with you, confidentially. There's no cost to find out where you stand.
Free case review Contact- HIE after birth: a guide for parents (you are here)
- "It was five days before I held her": the first week in NICU
- "Moderate, then mild after the MRI": what the grade means
- "My baby wasn't cooled"
- "The MRI says basal ganglia": reading the results
- "Still on the NG tube": feeding after HIE
- "Wait and see": the first two years
- "Tucked thumbs, head lag, stiff legs"
- Early intervention and the NDIS
- "Why didn't they do a caesarean sooner?"
- "The notes don't match what I saw"
- "They said there's no case because he's fine"
- "How long do we have?"
- "I keep replaying the birth"
- Pregnancy after HIE
- "I'm a nurse and I'd never heard of HIE"
More on birth injuries: birth trauma and obstetric negligence
References
- NSW Agency for Clinical Innovation. Hypoxic ischaemic encephalopathy in newborns: recognition, monitoring and early management. Clinical practice guide. Sydney: ACI; June 2024. aci.health.nsw.gov.au
- Queensland Clinical Guidelines. Hypoxic-ischaemic encephalopathy (HIE), July 2026. health.qld.gov.au
- Clinical Excellence Commission. NSW Consensus Statement: Newborn Hypoxic Ischaemic Encephalopathy. cec.health.nsw.gov.au
- Jacobs SE, Berg M, Hunt R, Tarnow-Mordi WO, Inder TE, Davis PG. Cooling for newborns with hypoxic ischaemic encephalopathy. Cochrane Database of Systematic Reviews 2013, CD003311. cochranelibrary.com
- Alternative diagnoses in neonates undergoing therapeutic hypothermia for presumed hypoxic–ischemic encephalopathy. PubMed Central
- Novak I, Morgan C, Adde L, et al. Early, accurate diagnosis and early intervention in cerebral palsy: advances in diagnosis and treatment. JAMA Pediatrics 2017;171(9):897–907. PubMed Central
- Royal Australian and New Zealand College of Obstetricians and Gynaecologists. Intrapartum Fetal Surveillance (C-Obs 1), 5th edn, September 2025. ranzcog.edu.au
- NSW Health. Policy Directive PD2020_047, Incident Management. health.nsw.gov.au
- Australian Commission on Safety and Quality in Health Care. Australian Open Disclosure Framework, June 2026. safetyandquality.gov.au
- Legislative Council Select Committee on Birth Trauma (NSW). Birth trauma. Report, 2024. parliament.nsw.gov.au
- National Disability Insurance Agency. What the early childhood approach is. ndis.gov.au
- Civil Liability Act 2002 (NSW), s 5O. legislation.nsw.gov.au
- Rogers v Whitaker (1992) 175 CLR 479; [1992] HCA 58. austlii.edu.au
Stories in this article are composites drawn from many families' experiences and have been changed so that no one can be identified. They do not describe any individual client.
Written by Dr Rosemary Listing, PhD (Law). Rosemary is a medical negligence lawyer and Of Counsel at Peter Evans & Associates. She has practised since 2013 and worked on many hundreds of claims, including for families after injuries at birth. Her doctoral research examined patterns of failure in medical negligence, and she is a Sessional Lecturer in Health Law at the University of Newcastle. She is responsible for all content published under her name.
Rosemary is not medically qualified. Clinical information in this guide is drawn from, and checked against, the NSW, Victorian and Queensland neonatal guidelines and the research listed in the references. Legal information reflects the law as at the review date.
Last updated 28 October 2026. First published 28 October 2026. Next review April 2027.
Cite this article: Listing, R. (2026, October 28). HIE After Birth: A Guide for Parents, From the Cooling Cot to the Answers. Reframe Legal. https://reframelegal.com/hie-birth-injury/
This guide is general information only. It isn't medical or legal advice about your situation, and reading it doesn't create a lawyer and client relationship. If you are worried about your baby, speak to your baby's medical team. If you are in crisis, call 000 or Lifeline on 13 11 14. Legal services are provided by Peter Evans & Associates.